

To annual or not to annual, that is the question.
In our office, we have heard lots of language devoted to the annual visit. we have heard them called "yearlies", " annual exams", "checkups" and "my favorite time of year". We sometimes find patients dreading it beforehand, but mentioning afterwards that it was really worthwhile.
For our office, it is not only about ensuring that girls and women stay on track with recommended screening procedures; it is about evaluating where they are with their self care, including nutrition, fitness, and sleep. Most importantly, we discuss a comprehensive and detailed plan of optimal health maintenance for the upcoming year. For the many women who we have seen for many years running, we are health base camp.
Controversy
In this era of scientific skepticism and budget shortfalls, there has been significant discussion in the press about whether or not the annual visit is worth it. With the cost of medicine being a concern, and new insurance regulations around every corner, it is important to understand the real recommendations. .
The annual exam became a fixture of American medical practice in the 1940s. By the 1980s, people and mayors started questioning its utility. Governing bodies such as the USPTF ( The IS Preventive Services task force questioned its utility, recommending more of an as needed approach, but health advocacy groups and scientific bodies such as ACOG, the American College of Obstetricians and Gynecologists pushed back, citing repeated concerns regarding study design and interpretation.
For a time, the lay press predominantly took this out of context and declared annual exams were no longer necessary. Making matters worse, this came on the heels of a badly conceived and badly reported recommendation from the USPSTF to curtail mammogram frequency.
Witness the cynicism in this article from a physician, Elisabeth Rosenthal, writing for the New York Times:
http://www.nytimes.com/2012/06/03/sunday-review/lets-not-get-physicals.html?pagewanted=all&_r=0
In this article she states,
"I finished my medical training in 1989. I respect my doctors, but I see them only when I’m sick. I religiously follow schedules for the limited number of screening tests recommended for women my age — like mammograms every two years and blood pressure checks — but most of those do not require a special office visit."
Perhaps because she is a physician she can show up to the radiology department and get a mammogram or slip in and out of the office for a pap or blood pressure check. Perhaps she thinks because she is a physician she is beyond having her history taken or her health maintenance behaviors assessed. Traditional medical training requires a history, pertinent aspects of the physical exam, and pertinent diagnostic studies followed by an assessment, plan and discussion with the patient, not just stopping by for a diagnostic procedure. In her New York Times article, Dr. Rosenthal cites Allen Brett, MD, a professor of clinical internal medicine at the University of South Carolina, who comments thus:
“If you ask gynecologists why they still do yearly Pap smears they’ll say things like: Patients expect it; It keeps patients coming back; It’s what we do in an OB-GYN visit.”
I have several comments. How qualified is a university professor of internal medicine to comment on the yearly visit between a woman and her gynecologist in the private practice setting? His practice environment consists of a formal system of staffing by residents and medical students who do most of the direct patient care. Residents and medical students change every year and, though well educated and hardworking, they do not provide the continuity or the professional and life experience to shepherd an adult woman through the many life events that are seen in Obstetrics and Gynecology.
Intimations that OB/GYNs ask patients back for annual exams to make more money are unprofessional and groundless, especially since we could generally make more money seeing problem oriented patients, a fact which Dr. Brett would know if he were familiar with managing a practice. OB/GYNs see patients back for annuals because ACOG recommends it on an evidentiary basis. We also do it because it is satisfying professionally for us, known that through these visits, we actually have a shot at improving a patient’s health and quality of life.
The American College of Obstetrics and Gynecology (ACOG) position on annual exams:
ACOG has an entire document devoted to the "well woman visit" and its importance, Committee Opinion Number 755, reaffirmed 2024. Included in its abstract is the following:
"A well-woman visit provides an excellent opportunity to counsel patients about maintaining a healthy lifestyle and minimizing health risks. Given the shifting and complex landscape of care, in which many women may not receive all the recommended preventive services, obstetrician–gynecologists have an opportunity to contribute to the overall health and well-being of women throughout the lifespan by providing recommended preventive services and counseling. Taking a comprehensive history (specifically obtaining detailed information on symptoms and past medical and gynecologic history) will inform if certain components of the physical examination, including breast or pelvic examination, are indicated at that visit and will inform shared decision making for these examinations. Family history should be used as a risk assessment tool and should be completed and updated regularly to ensure the most comprehensive assessment of a woman’s personal risk factors. Another key component of a well-woman visit for a reproductive-aged woman is the development and discussion of her reproductive life plan to ensure that medical testing and treatments provided are aligned with her current and future plans. Obstetrician–gynecologists provide care for women across the lifespan, and periodic well-woman visits are appropriate and necessary for perimenopausal women and postmenopausal women as well. This Committee Opinion has been revised to reflect updated guidance on components of the physical examination and new sources for well-woman preventive services." (American College of Obstetricians and Gynecologists)
A well woman visit may or may not include screening for breast and cervical cancer. Please see details below.
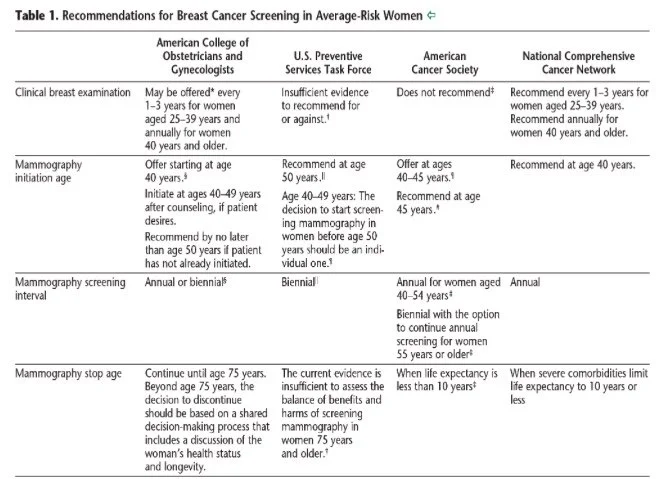
Breast Cancer Screening
Based on available evidence ACOG, National Comprehensive Cancer Network , the USPTF, and the American Cancer Society recommend offering periodic clinical breast exams and mammograms at slightly different ages and frequencies:
Cervical Cancer Screening using the Pap smear and HPV (Human Papilloma Virus) testing
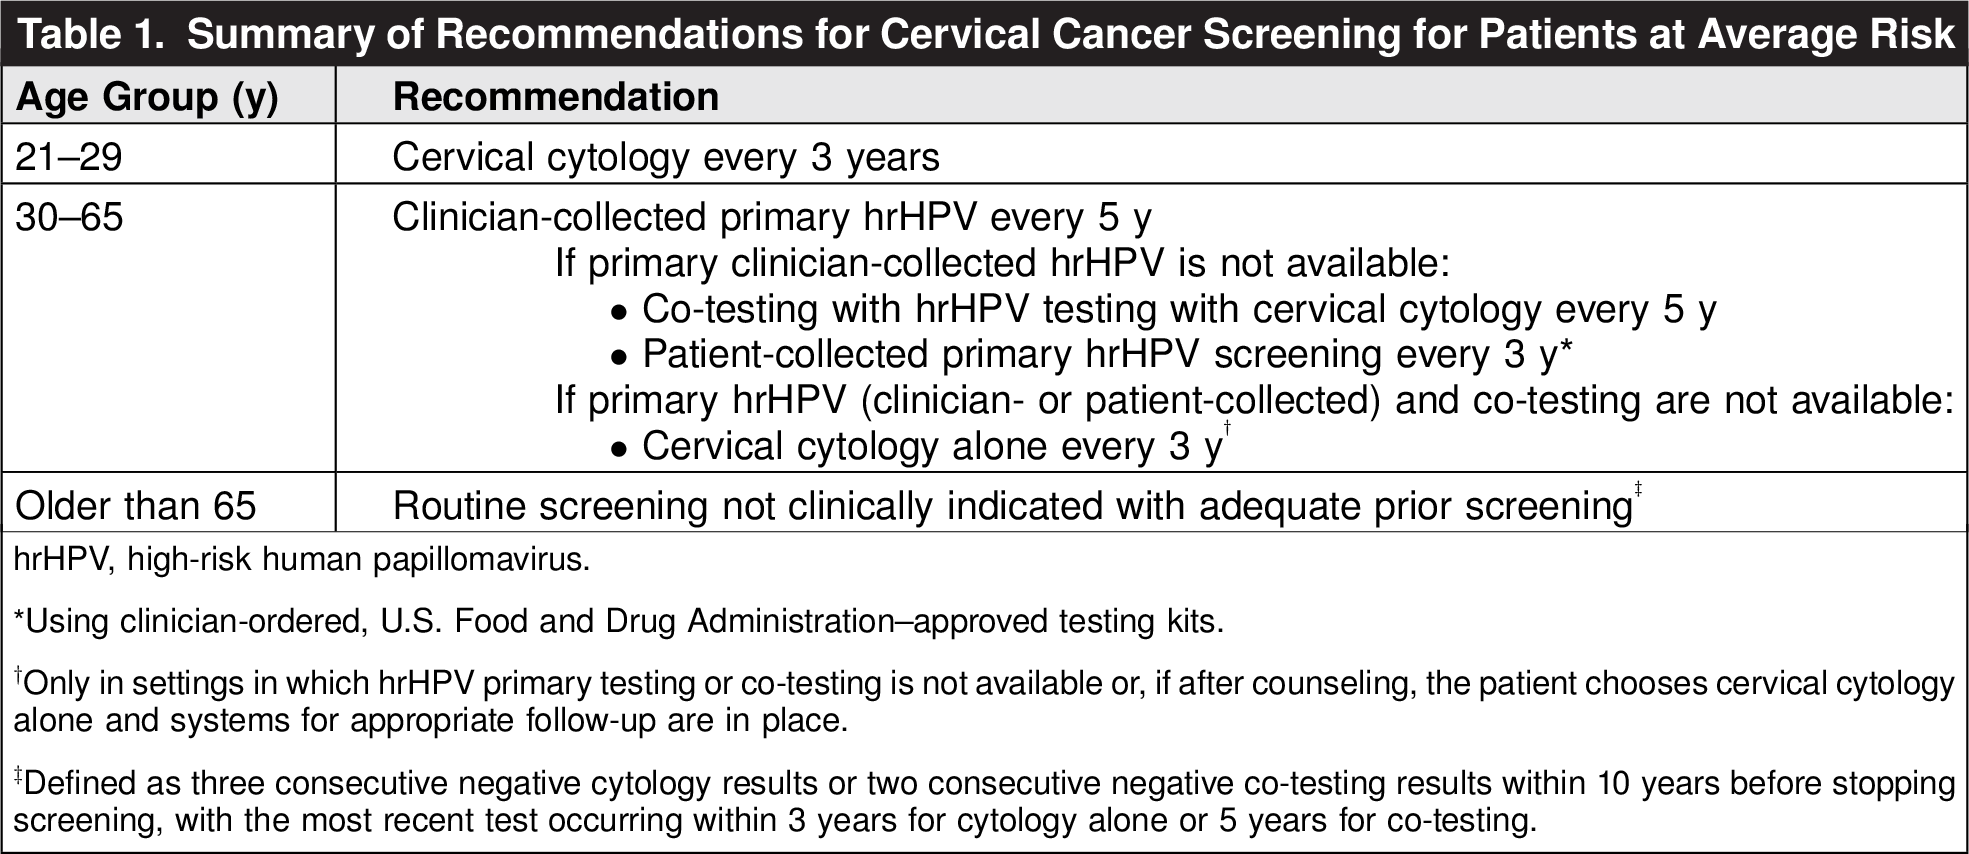
It is critical to bear in mind that these recommendations are for women “ at average risk” for cervical cancer. Those which may have elevated risk include smokers, those with past history of HPV disease such as cervical dysplasia, genital warts, those with other STIs (sexually transmitted infections), multiple partners, those who have not had recommended screenings, and those with compromised immune systems.
Details about the time and content of the annual exam
Annual visits with the OB/Gyn include screening, evaluation and counseling about illness, prevention and health maintenance.
Annual visits with the OB/Gyn should begin somewhere between 13-15 years of age. Please see our section on Adolescent Gyn for more details on the younger years.
The speculum exam part of the pelvic exam is not generally indicated until 21 years of age, when the first pap is due. However, specific symptoms or conditions may require a speculum exam to be conducted earlier. Speculum exam is not necessarily a prerequisite for prescribing birth control pills or checking for STDs, either of which may be needed in women under the age of 21.
The pelvic exam itself consists of three elements: the external exam, the internal speculum exam of the vagina and the cervix, and the bimanual exam. During the bimanual exam, the examiner inserts two fingers in the vagina and the other hand on the patient's abdomen, enabling her to palpate the uterus and usually the ovaries as well. The examiner can then discern the size, contour, mobility, and tenderness of these pelvic organs. For those over 40 or with certain symptoms, a rectal exam may also be done.

The annual visit is not to be confused with the pelvic exam or Pap smear.
The visit is a multifaceted doctor patient encounter which includes history, a tailored physical exam which may or may not include a pelvic exam, as well as discussion about any needed screening or diagnostic studies like blood work or imaging. It also includes a detailed assessment of prevention and health maintenance measures like vaccinations, nutrition, fitness and sleep. Finally the visit should identify any mental health needs and initiate the process of addressing them.
We chronicle the successes of the year. We tackle problems together. Despite the controversy and confusion over the annual checkup, we believe it is a well founded holistic practice. Honestly, we usually have a great time with our patients.
Welcome to your annual!

References about the Annual Exam:
American College of Obstetricians and Gynecologists, Well-woman visit. Committee Opinion No. 534. Obstet Gynecol 2012;120:421-4
Bloomfield, Hanna E MD, MPH and Wilt, Timothy J MD, MPH. Evidence Brief: Role of the Annual Comprehensive Physical Examination in the Asymptomatic Adult, PMID: 22206110
Darves, Bonnie, Rethinking the Value of the Annual Exam, January ACP Internist, copyright © 2010 by the American College of Physicians
Rosenthal, Elisabeth, MD, Let's (Not) Get Physicals, The NewYork Times Sunday Review, June 2, 2012
USPSTF, Guide to Clinical Preventive Services, Second Edition , http://odphp.osophs.dhhs.gov/pubs/guidecps/default.htm